

If an older adult suddenly becomes confused, unusually agitated, or withdrawn, and you also notice burning during urination, cloudy or foul-smelling urine, new incontinence, or a fever, contact a clinician the same day. Those two patterns together, sudden mental change plus urinary symptoms, are the combination most likely to signal a urinary tract infection in seniors. Skip the wait-and-see approach if there's also a high fever, very low blood pressure, a racing heart, or extreme lethargy; those point toward possible sepsis and need emergency care right away.
TL;DR:
- Many older adults with UTIs may not develop a fever, so caregivers should rely on behavioral and physical changes rather than temperature alone.
- Sudden mental confusion or behavioral shifts in seniors often signal infections like UTIs but require careful comparison to their baseline to identify real issues.
- Urinary symptoms such as burning, urgency, cloudy urine, or blood are common, but systemic signs like flank pain or severe confusion indicate more serious infections needing prompt medical attention.
- Risk factors for UTIs in seniors include urinary retention, incontinence, dehydration, poor hygiene, catheter use, and chronic conditions like diabetes, which caregivers can influence through daily support.
- Documenting small daily changes, including behavior, sleep, and urine appearance, helps clinicians differentiate between benign issues and serious infections requiring urgent care.
Table of Contents
- Classic Physical Signs of a UTI in Seniors
- Mental and Behavioral Signs: When Confusion Signals Something Is Wrong
- Why Older Adults Face Higher UTI Risk
- Diagnosis and Testing: What the Numbers Don't Tell You
- What to Do Right Now: Steps and Red Flags
- Prevention: Daily Habits That Lower UTI Risk
- A Caregiver's Daily Monitoring Checklist
- The Caregiver's Balancing Act
- How In-Home Care Supports Early UTI Detection
- Sources
- FAQ
Classic Physical Signs of a UTI in Seniors
Urinary tract infection symptoms in older adults often start the same way they do in younger people, even though the presentation frequently gets more complicated as age advances. Recognizing the physical baseline first makes it much easier to spot when something has shifted.
Watch for these classic urinary symptoms:
- Burning or pain when urinating (dysuria)
- Sudden urgency, needing to go right away with little warning
- Frequent trips to the bathroom, often passing only small amounts each time
- A nagging feeling that the bladder never fully empties
- New or suddenly worse incontinence in someone who was previously continent, or more accidents than usual
Urine appearance tells its own story, and its caregiver is well positioned to notice during routine toileting help. Cloudy urine, a stronger or more unpleasant odor than normal, and darker or tea colored urine can all point to infection. Blood in the urine, even a faint pink tinge, warrants a call to the doctor regardless of other symptoms.
Systemic signs matter just as much as the local urinary ones. Fever, chills, nausea, and pain in the lower abdomen (the area right above the pubic bone) or in the flank, the side of the back below the ribs, often accompany a more advanced infection. Flank pain in particular can suggest the infection has traveled up toward the kidneys, which raises the stakes considerably.
Here's the part that trips up a lot of caregivers, including experienced ones: fever is often absent. Cleveland Clinic notes that classic urinary symptoms still show up in older adults, but the systemic signs that usually flag infection in younger patients, especially fever, don't always appear. One review found fever present in a small share of a cohort of older adults with confirmed UTIs and delirium. That means a normal temperature reading tells you almost nothing on its own. A senior can have a genuine, serious infection and still register 98.2°F on the thermometer.
This is exactly why caregivers who spend real time with an older adult, whether that's a daughter checking in every evening or a professional caregiver present for a scheduled shift, catch things a single doctor's visit might miss. You know what "normal" looks like for this specific person, and that baseline is the single most useful diagnostic tool in your hands.
Mental and Behavioral Signs: When Confusion Signals Something Is Wrong
Sudden confusion, disorientation, unexplained agitation, unusual withdrawal, new sleepiness that doesn't fit the person's routine, or even hallucinations and emotional outbursts can all be signs of a urinary tract infection in an elderly adult, sometimes with no urinary symptoms at all, as detailed in Sudden Confusion in Elderly Causes: A Calm Guide | Helping Mom LLC. This atypical presentation trips up families constantly, because it doesn't look like an infection. It looks like a bad day, or a sign that dementia has suddenly worsened.
A 2022 systematic review found a real, measurable relationship between UTIs and delirium in older adults, reporting delirium in a significant share of older adults with a confirmed UTI. That's a meaningful share of cases where the brain, not the bladder, sends the first distress signal.
The mechanism behind this isn't mysterious once you understand it. Experts at Cedars-Sinai explain that UTIs can trigger delirium through inflammatory signals released during infection, signals that interfere with normal brain function. Older brains, especially those already coping with mild cognitive decline, are simply more vulnerable to that disruption than younger ones.
Here's how to tell delirium apart from ordinary dementia progression:
- Check the timeline. Delirium comes on fast, over hours or a few days. Dementia decline happens over months or years.
- Watch for fluctuation. Someone with delirium might seem sharp in the morning and completely lost by evening. Dementia tends to be more consistent day to day.
- Compare against a real baseline. Write down how this person normally sleeps, how oriented they usually are, and what they can do for themselves on an average day, before anything seems off.
- Note any sudden loss of function. Can they still feed themselves? Wash their own face? A new inability to do either is a red flag worth mentioning to a doctor.
- Rule out other causes before assuming infection. Confusion alone is not proof of a UTI. Medication changes, low blood sugar, dehydration, and other infections can all cause the same picture, and a clinician needs to sort through the possibilities rather than jump straight to antibiotics.
Pro Tip: Keep a simple note on your phone with three lines: how they slept, whether they knew what day it was, and whether they managed their usual morning routine unassisted. That tiny baseline log becomes incredibly valuable the moment something changes, because you'll have real data instead of a vague feeling that "something's different."
Why Older Adults Face Higher UTI Risk
Age-related physical changes stack the deck against older adults in ways that have nothing to do with hygiene or bad luck. In postmenopausal women, vaginal atrophy changes the local tissue environment and reduces natural defenses against bacteria. The immune response weakens overall with age, making it harder for the body to clear bacteria that a younger immune system would handle without issue. Bladder emptying also tends to become less complete, leaving residual urine that acts like a breeding ground.
Common risk factors that raise UTI risk in seniors include:
- Indwelling urinary catheters, which introduce a direct pathway for bacteria
- Urinary retention, often tied to an enlarged prostate in men
- Incontinence, particularly when skin and clothing stay damp for extended periods
- Chronic constipation, which puts pressure on the bladder and disrupts normal emptying
- Diabetes, which affects immune function and can lead to higher sugar levels in urine
- Dehydration, which concentrates urine and reduces the natural flushing action that clears bacteria
- Poor perineal hygiene, especially for those with limited mobility or dexterity
- Living in a nursing home or assisted living setting, where infection exposure runs higher
The good news: several of these are things a caregiver can influence directly. Encouraging fluids, staying ahead of constipation, offering timely bathroom help instead of waiting for a request, and assisting with proper hygiene all fall squarely within a caregiver's reach. Catheter management, prostate issues, and diabetes control, on the other hand, need ongoing medical oversight and shouldn't be handled through home adjustments alone.
Diagnosis and Testing: What the Numbers Don't Tell You
Urine tests confirm a lot, but they don't tell the whole story in older adults, and that gap causes real confusion for families expecting a clean yes-or-no answer. Clinicians typically start with a dipstick test, which checks for leukocyte esterase (a marker of white blood cells fighting infection) and nitrites (a byproduct of certain bacteria). A positive dipstick often leads to a full urinalysis and, frequently, a urine culture to identify the specific bacteria involved.
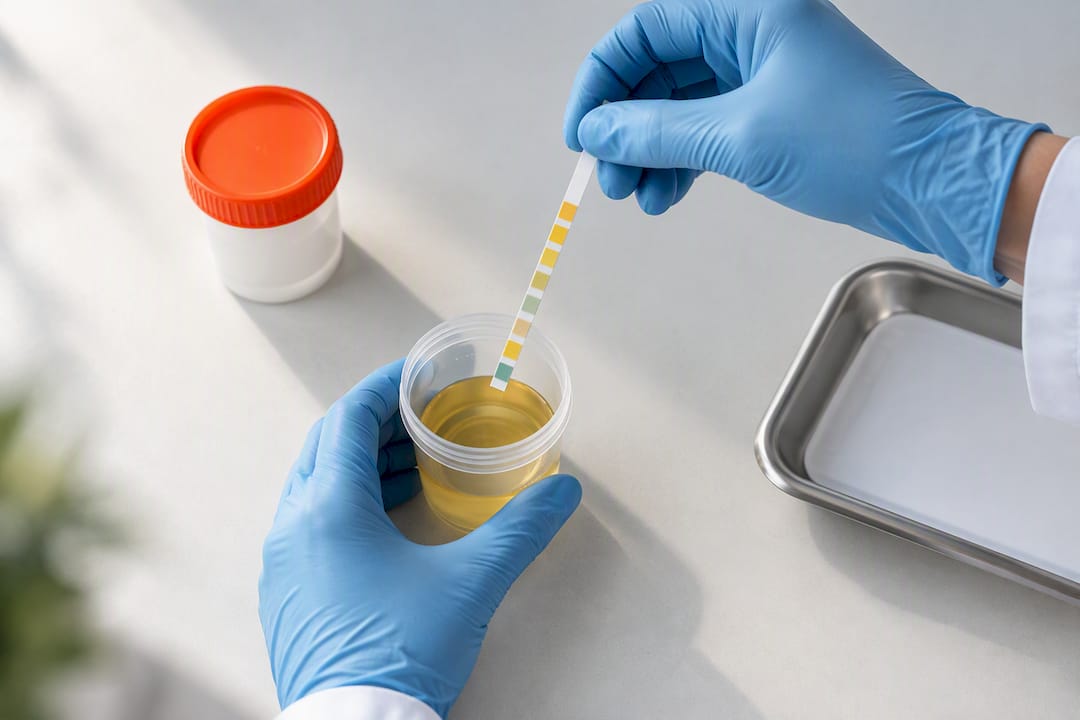
Here's where it gets complicated. A large share of older adults, especially women in long-term care, carry bacteria in their urine without any infection at all. This is called asymptomatic bacteriuria, and it's genuinely common, not a lab error or a fluke. Treating it with antibiotics when there are no actual symptoms doesn't help and can cause harm, including antibiotic resistance and unnecessary side effects. This is exactly why a positive urine culture by itself, without matching symptoms, isn't a green light for treatment.
What clinicians weigh before diagnosing a UTI in an older adult:
- Dipstick results (leukocyte esterase and nitrites) as an initial screen
- Full urinalysis for white blood cells, red blood cells, and bacteria counts
- Urine culture to confirm the specific organism and guide antibiotic choice if treatment is warranted
- The patient's actual symptoms, weighed against test results rather than in isolation
- Recent changes in function or behavior, particularly in patients who can't clearly describe their own symptoms
That last point matters enormously for anyone caring for a person with dementia or significant communication limits. A diagnostic meta-analysis covering 15 studies and over 12,000 participants found that many classic symptoms, like nocturia or abnormal vital signs, actually have limited value for confirming a UTI in older outpatients. What predicted infection far more reliably was sudden functional decline: new disability in feeding oneself carried a positive likelihood ratio of 11.8, and new difficulty washing one's own face carried a likelihood ratio of 6.84. In plain terms, a sudden "I can't do this anymore" moment is a stronger clue than most textbook urinary symptoms.
That's a genuinely useful thing for caregivers to know, because it means the small, everyday observations you make, whether someone suddenly needs help with a fork they managed independently yesterday, carry real diagnostic weight. Communication-limited patients can't always report burning or urgency, but they can show you a sudden drop in function, and that's worth documenting and reporting just as seriously as a classic symptom.
What to Do Right Now: Steps and Red Flags
When you notice a change, whether it's physical, mental, or both, act in this order.
- Write down exactly what changed and when. Note the time you first noticed it, and describe it specifically: "stopped recognizing me around 3pm" carries far more useful information than "seemed off today."
- Take a temperature reading, even though a normal result doesn't rule anything out.
- Offer fluids and help with a bathroom trip if needed, both to support hydration and to observe urine appearance directly.
- Check for recent medication changes. New prescriptions, dosage adjustments, or missed doses can mimic or mask infection symptoms.
- Collect a clean-catch urine sample if a clinician's office asks for one before the visit; ask the office for specific instructions since technique affects accuracy.
- Call the clinician's office and describe the change plainly, including anything from your baseline notes.
Emergency red flags that need urgent or emergency care immediately:
- A high fever, particularly combined with chills or shaking
- Flank pain or severe abdominal pain, which can indicate the infection has reached the kidneys
- Very low blood pressure or fainting
- A markedly rapid heart rate
- Severe confusion or a noticeably reduced level of consciousness
- Any combination of the above, which can point toward urosepsis, a life-threatening complication where infection spreads into the bloodstream
Pro Tip: Before a clinician visit, put together a one-page summary: current medications, a plain description of the person's normal baseline behavior, what's changed and when, and any urine sample you collected. Handing over organized information saves precious time and helps the clinician reach the right diagnosis faster, especially in an urgent care or emergency room setting where visits move quickly.
Left untreated, a UTI in an older adult can progress well beyond bladder discomfort. Infection can travel to the kidneys, causing lasting kidney damage, or spread into the bloodstream as urosepsis, a genuine medical emergency with a real risk of death if not caught quickly. That escalation is precisely why sudden confusion or a rapid behavioral shift deserves the same urgency as a physical symptom, not less.
Prevention: Daily Habits That Lower UTI Risk
Consistent hydration is the single most practical thing a caregiver can influence day to day, since concentrated urine gives bacteria more opportunity to take hold and multiply. Encourage water throughout the day rather than large amounts all at once, and keep an eye on dehydration in seniors, since older adults often lose their natural thirst cues and won't ask for fluids the way a younger person would.
Practical daily prevention steps:
- Offer fluids regularly throughout the day, not just at mealtimes
- Provide scheduled toileting assistance rather than waiting for a request, especially for anyone with mobility limits
- Support proper perineal hygiene, wiping front to back, and prompt changes for anyone using incontinence products
- Address constipation early, since a full bowel puts pressure on the bladder and interferes with complete emptying
- Review medications regularly with a doctor or pharmacist, since some drugs affect bladder function or hydration status
- Keep diabetes well managed, since elevated blood sugar creates a friendlier environment for bacteria
- Follow proper catheter care protocols exactly as instructed for anyone using one
Pro Tip: If UTIs keep coming back, three or more in a year, bring that pattern to the clinician directly rather than treating each episode as a separate event. Recurrent infections sometimes call for a different approach, like a longer-term prevention strategy or a closer look at anatomical or medication-related contributors.
Simple documentation makes a real difference here too. A short daily note covering orientation, sleep, appetite, and urine appearance, shared at the very first sign of trouble, helps a clinician triage faster and often shortens the time to an accurate diagnosis. It doesn't need to be elaborate. Consistency beats detail.
A Caregiver's Daily Monitoring Checklist
A short daily check, done consistently, catches changes before they become emergencies. Compare each item against the person's actual baseline, not a generic standard.
Track these each day:
- Orientation: Do they know the day, where they are, and who you are?
- Sleep pattern: More sleep than usual, or noticeably less?
- Appetite and fluid intake: Eating and drinking normally, or refusing?
- Urine appearance and odor: Any cloudiness, strong smell, or unusual color?
- Fever or feeling warm to the touch
- ADL performance: Can they still dress, wash, and feed themselves as usual?
A trained in-home caregiver can extend this kind of observation across a full shift rather than a quick morning check, handling toileting assistance, hydration reminders, medication reminders, and transportation to medical appointments while keeping respectful, private notes a family can bring straight to a clinical visit. That kind of steady, dignity-first presence often catches subtle shifts, a slower response, a skipped meal, days before a family member visiting once a week would notice anything at all.
The Caregiver's Balancing Act
Trust sudden change. If someone who was sharp and steady yesterday is foggy, agitated, or oddly withdrawn today, that's real information, not an overreaction on your part. Get it in front of a clinician instead of waiting to see if it passes on its own.
At the same time, resist the urge to label every off day a UTI. Dehydration, a new medication, poor sleep, or plain fatigue can all produce a similar picture, and reflexively assuming infection leads to unnecessary testing and, sometimes, unnecessary antibiotics for bacteria that were never causing harm in the first place. The most useful thing you can do isn't diagnosing it yourself. It's documenting exactly what changed, when, and how it compares to that person's normal, then handing that information to someone qualified to sort out the cause. Good notes, not guesses, are what actually move a diagnosis forward.
— Cameron
How In-Home Care Supports Early UTI Detection
Tucsonshs is a practical alternative to relying on occasional family check-ins or a rushed weekly visit. Caregivers who are seniors themselves spend real hours with your loved one, which means they catch the kind of subtle shift, a skipped meal, a slower response, a new confusion, that's easy to miss when you're only checking in by phone.

Companionship visits build the baseline knowledge that makes sudden changes obvious rather than easy to explain away. Trained caregivers can assist with toileting and personal care, offer medication reminders so nothing gets missed or doubled up, handle transportation to medical appointments, and provide respite care so family caregivers aren't stretched thin trying to do it all alone. If recurrent UTIs have become a pattern, or hydration and toileting have gotten harder to manage safely at home, or a loved one with dementia has started showing sudden, unexplained changes, that's the point to consider bringing in extra support.
Visit the full lineup of in-home care services to see what fits your situation, or reach out to Tucsonshs directly to talk through scheduling and start a consultation.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Urinary Tract Infection Induced Delirium in Elderly Patients: A Systematic Review
- Symptoms of Urinary Tract Infections in Older Adults
- How urinary tract infections can trigger delirium and worsen dementia
FAQ
What are the emotional symptoms of a UTI in an older adult?
Emotional symptoms can include sudden agitation, unusual withdrawal, irritability, tearfulness, or emotional outbursts that seem out of character. These often appear alongside confusion and are part of the delirium pattern linked to UTIs, so any sudden emotional shift is worth mentioning to a clinician.
At what age does a UTI start causing confusion?
There's no single age cutoff, but the risk of infection-related confusion rises significantly in adults over 65, especially those with existing cognitive impairment. A 2022 systematic review found delirium in roughly 28.9% of older adults with a confirmed UTI.
Can UTIs cause low blood pressure in elderly people?
Yes, in more severe cases, a UTI can progress to urosepsis, where infection spreads into the bloodstream and blood pressure drops sharply. A sudden drop in blood pressure alongside other UTI symptoms is a medical emergency and needs immediate care.
What can mimic a UTI in an elderly person?
Dehydration, new medications, constipation, other infections, and normal dementia progression can all produce symptoms that look like a UTI, including confusion and behavior changes. This is exactly why clinicians rely on testing and functional changes together rather than symptoms alone, and why Cleveland Clinic cautions against treating confusion as automatic proof of infection.
Does Tucsonshs help with UTI prevention at home?
Caregivers assist with hydration reminders, toileting support, medication reminders, and transportation to medical appointments, all of which support early detection and prevention. Current pricing and service details are available directly on the Tucsonshs services page.